
[Jun 21, 2026] AB-Abdomen Dumps Full Questions - Exam Study Guide
ARDMS RDMS Free Certification Exam Material from Exam4Tests with 165 Questions
ARDMS AB-Abdomen Exam Syllabus Topics:
| Topic | Details |
|---|---|
| Topic 1 |
|
| Topic 2 |
|
| Topic 3 |
|
| Topic 4 |
|
NEW QUESTION # 88
Which vascular condition is most consistent with patent cutaneous para-umbilical channels and portal hypertension?
- A. Esophageal varices
- B. Caput medusae
- C. Coronary vein varices
- D. Splenic vein varices
Answer: B
Explanation:
Caput medusae refers to dilated paraumbilical veins due to portal hypertension. When portal venous pressure rises, collateral channels may open along the ligamentum teres and recanalized paraumbilical vein, resulting in visible dilated veins radiating from the umbilicus.
* Esophageal varices (B) are gastroesophageal collaterals.
* Coronary vein varices (C) involve gastric veins.
* Splenic vein varices (D) are typically localized to the splenic hilum.
Reference Extracts:
* Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound. 5th ed. Elsevier, 2017.
* Gore RM, Levine MS. Textbook of Gastrointestinal Radiology. 4th ed. Saunders, 2015.
-
NEW QUESTION # 89
Which finding is helpful to differentiate postsurgical breast scarring from a recurrent tumor?
- A. Architectural distortion
- B. Associated skin thickening
- C. Irregular hypoechoic area
- D. Absent Doppler signal
Answer: D
Explanation:
Postsurgical breast scarring may appear hypoechoic and irregular but typically shows no internal vascularity on Doppler imaging. In contrast, recurrent tumors generally exhibit increased internal vascular flow due to neovascularization. Therefore, absent Doppler signal helps suggest scar tissue rather than malignancy.
According to Stavros' Breast Ultrasound:
"The absence of internal Doppler flow favors scar tissue, whereas recurrent malignancy typically demonstrates internal vascularity." Reference:
Stavros AT. Breast Ultrasound. Lippincott Williams & Wilkins, 2004.
AIUM Practice Parameter for Breast Ultrasound, 2020.
-
NEW QUESTION # 90
Which of the following is a possible early complication of a renal transplant?
- A. Ureterocele
- B. Transplant artery stenosis
- C. Acute tubular necrosis
- D. Transitional cell carcinoma
Answer: C
Explanation:
Acute tubular necrosis (ATN) is the most common cause of early graft dysfunction following renal transplantation. It results from ischemia-reperfusion injury during the transplantation process. Ultrasound findings may be nonspecific but Doppler may show elevated resistive indices.
Ureterocele (A) is a congenital anomaly.
Transplant artery stenosis (C) is a late complication.
Transitional cell carcinoma (D) is rare and not typically an early complication.
Reference Extracts:
Middleton WD, Kurtz AB, Hertzberg BS. Ultrasound: The Requisites. 3rd ed. Elsevier, 2015.
Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound. 5th ed. Elsevier, 2017.
-
NEW QUESTION # 91
Which neoplasm is a benign tumor of the spleen?
- A. Metastasis
- B. Angiosarcoma
- C. Lymphoma
- D. Littoral cell angioma
Answer: D
Explanation:
Littoral cell angioma is a rare, benign vascular tumor of the spleen, arising from the littoral cells lining the splenic sinusoids. In contrast, lymphoma, metastasis, and angiosarcoma are malignant splenic neoplasms.
According to WHO Classification and Rumack's Diagnostic Ultrasound:
"Littoral cell angioma is a rare benign vascular neoplasm of the spleen with characteristic imaging findings." Reference:
Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound. 5th ed. Elsevier, 2017.
WHO Classification of Tumours of the Digestive System, 5th ed., IARC, 2019.
-
NEW QUESTION # 92
Which finding is most likely demonstrated in this abdominal wall image of a patient with a history of atrial fibrillation?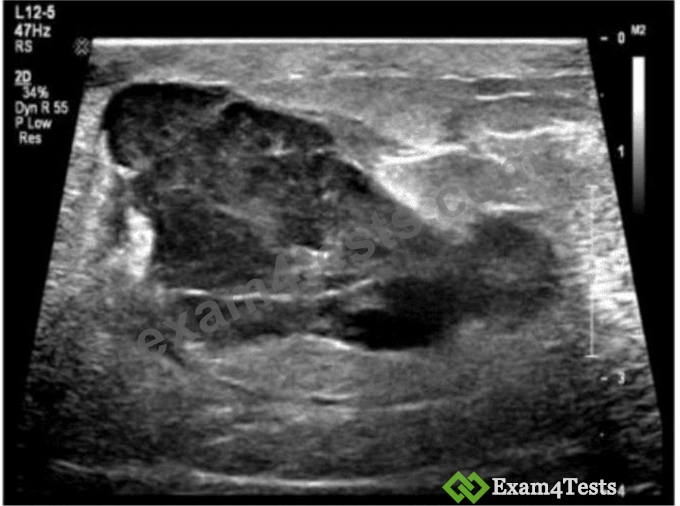
- A. Hernia
- B. Lipoma
- C. Hematoma
- D. Abscess
Answer: C
Explanation:
The ultrasound image demonstrates a complex, heterogeneous hypoechoic collection within the abdominal wall, with mixed echogenicity and ill-defined margins. The lesion appears to contain internal debris but lacks definitive signs of vascularity or air (which would be seen in an abscess). There is no peristalsis, herniated bowel, or fat to suggest hernia.
Given the history of atrial fibrillation - a condition commonly treated with anticoagulation therapy (e.g., warfarin, apixaban) - this clinical background raises high suspicion for a rectus sheath or abdominal wall hematoma.
Key ultrasound features of hematomas:
* Early (acute): hyperechoic or heterogeneous
* Chronic/resolving: complex or cystic with fluid-debris levels
* No internal vascularity on Doppler
* May be confined to muscle or fascial planes
This is consistent with a hematoma, particularly in patients on anticoagulation therapy.
Comparison of answer choices:
* A. Hernia - typically shows bowel or fat with movement/peristalsis passing through a fascial defect.
* B. Lipoma - usually homogeneous and echogenic, not complex or fluid-filled.
* C. Abscess - often presents as a complex fluid collection with peripheral hyperemia and possibly air, plus systemic signs of infection.
* D. Hematoma - Correct. The image and clinical history (anticoagulation due to atrial fibrillation) strongly support this diagnosis.
References:
Berman L, et al. Sonographic appearance and evolution of rectus sheath hematomas. AJR Am J Roentgenol.
1996.
Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound, 5th ed. Elsevier; 2017.
AIUM Practice Parameter for the Performance of Diagnostic Ultrasound Examinations of the Abdomen and Retroperitoneum (2020).
NEW QUESTION # 93
What is the normal Doppler waveform signature of the hepatic veins?
- A. Monophasic
- B. Triphasic
- C. Low resistant
- D. Turbulent
Answer: B
Explanation:
The normal hepatic vein Doppler waveform is triphasic, reflecting cardiac cycle variations in central venous pressure transmitted from the right atrium through the IVC. Loss of triphasicity may suggest elevated right atrial pressures or hepatic venous obstruction.
According to Rumack's Diagnostic Ultrasound:
"The normal hepatic vein waveform is triphasic due to transmitted right atrial pressure variations." Reference:
Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound. 5th ed. Elsevier, 2017.
AIUM Practice Parameter for Abdominal Vascular Ultrasound, 2020.
NEW QUESTION # 94
Which vessel is most likely to display hepatofugal flow in the presence of portal hypertension?
- A. Splenic vein
- B. Coronary vein
- C. Inferior epigastric vein
- D. Inferior vena cava
Answer: B
Explanation:
The coronary vein (left gastric vein) is a common collateral pathway in portal hypertension. It often becomes dilated and may demonstrate hepatofugal (reversed) flow as blood diverts from the high-pressure portal system into systemic collaterals.
According to Zwiebel's Introduction to Vascular Ultrasound:
"The left gastric (coronary) vein is a frequent site of hepatofugal flow in portal hypertension, reflecting collateral development." Reference:
Zwiebel WJ, Pellerito JS. Introduction to Vascular Ultrasound. 6th ed. Elsevier, 2019.
AIUM Practice Parameter for Portal Venous Doppler Ultrasound, 2020.
NEW QUESTION # 95
Which vessel is indicated by the arrow on this image?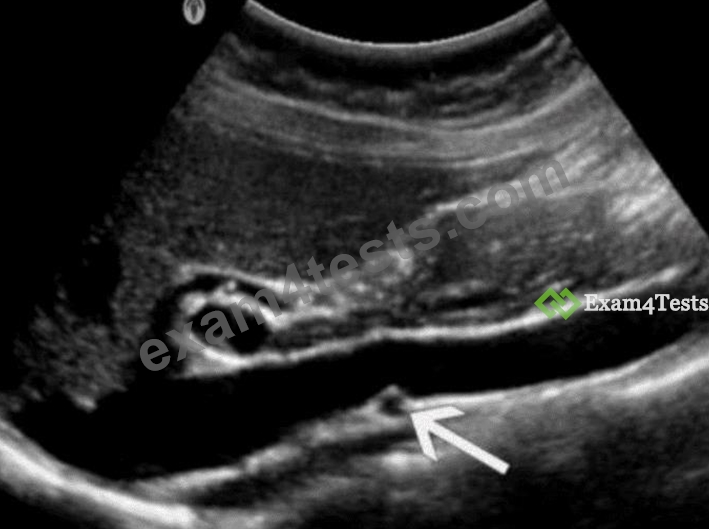
- A. Proper hepatic artery
- B. Left renal vein
- C. Right renal artery
- D. Superior mesenteric artery
Answer: D
Explanation:
The ultrasound image demonstrates a transverse view of the abdominal vasculature, where the arrow is pointing to a circular vascular structure anterior to the aorta and posterior to the body of the pancreas - consistent with the superior mesenteric artery (SMA).
The SMA originates from the anterior aspect of the abdominal aorta just below the level of the celiac trunk and courses anterior to the left renal vein and uncinate process of the pancreas. On transverse ultrasound, it is often seen in cross-section as a round, pulsatile structure with echogenic walls, situated just anterior to the aorta. This appearance is known as the "target sign" or "bull's-eye" appearance.
Vessel Position Landmarks (transverse plane):
* Aorta: Posterior and central
* SMA: Just anterior to the aorta
* Left renal vein: Passes between the aorta and SMA (nutcracker location)
* Right renal artery: Courses posterior to the IVC toward the right kidney Differentiation from other options:
* A. Proper hepatic artery: Typically visualized within the liver hilum (portal triad), not in this anatomic location.
* C. Left renal vein: Seen in transverse as a longer, oval structure crossing anterior to the aorta and posterior to the SMA.
* D. Right renal artery: Arises laterally from the aorta and courses posterior to the IVC - not visualized in this axial midline location.
References:
Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound. 5th Edition. Elsevier, 2018.
Chapter: Vascular Anatomy and Abdominal Vessels, pp. 471-475.
American Institute of Ultrasound in Medicine (AIUM) Practice Parameter for the Performance of an Ultrasound Examination of the Abdomen and/or Retroperitoneum, 2020.
Radiopaedia.org. Superior mesenteric artery: https://radiopaedia.org/articles/superior-mesenteric-artery
-
NEW QUESTION # 96
A patient presents with ampulla of Vater obstruction, distention of the gallbladder, and painless jaundice.
Which condition is most likely associated with these findings?
- A. Porcelain gallbladder
- B. Courvoisier sign
- C. Choledochal cyst
- D. Mirizzi syndrome
Answer: B
Explanation:
Courvoisier sign describes the clinical finding of painless jaundice combined with a palpable, distended gallbladder. This typically results from obstruction at the distal common bile duct, often due to pancreatic head carcinoma or cholangiocarcinoma, leading to bile accumulation and gallbladder distention. In contrast, Mirizzi syndrome involves compression of the common hepatic duct by an impacted stone in the cystic duct.
According to Rumack's Diagnostic Ultrasound and standard clinical references:
"Courvoisier sign refers to a palpable, enlarged gallbladder due to obstruction of the distal bile duct, often from malignancy." Reference:
Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound. 5th ed. Elsevier, 2017.
Moore KL. Clinically Oriented Anatomy. 8th ed. Wolters Kluwer, 2018.
-
NEW QUESTION # 97
Which arterial branches lie at the base of the renal pyramids?
- A. Interlobular
- B. Segmental
- C. Interlobar
- D. Arcuate
Answer: D
Explanation:
The arcuate arteries are located at the corticomedullary junction, arching over the base of the renal pyramids.
They form as the interlobar arteries reach the boundary between the cortex and medulla. The arcuate arteries give rise to the interlobular arteries, which supply the renal cortex.
* Segmental arteries (A) branch directly from the renal artery.
* Interlobar arteries (B) course between the renal pyramids.
* Interlobular arteries (D) extend into the cortex from the arcuate arteries.
Reference Extracts:
* Moore KL, Dalley AF, Agur AM. Clinically Oriented Anatomy. 7th ed. Lippincott Williams & Wilkins, 2013.
* Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound. 5th ed. Elsevier, 2017.
-
NEW QUESTION # 98
Which sonographic finding indicates the need for immediate surgical intervention following testicular trauma?
- A. Heterogeneity of the testicular parenchyma
- B. Intratesticular hematoma
- C. Discontinuity of the tunica albuginea
- D. Increased testicular vascularity
Answer: C
Explanation:
The tunica albuginea is a dense fibrous capsule surrounding the testis. Discontinuity of the tunica albuginea on ultrasound is diagnostic of testicular rupture - a urologic emergency that requires immediate surgical repair to preserve testicular function and viability. Early surgical intervention within 72 hours has a high success rate for testicular salvage (up to 90%).
* Intratesticular hematoma (A) may be managed conservatively if the tunica albuginea is intact.
* Heterogeneity of the parenchyma (C) indicates injury but not necessarily rupture.
* Increased vascularity (D) may be seen with inflammation or reperfusion but does not mandate surgery unless rupture is present.
Reference Extracts:
* Dogra VS, Bhatt S. "Acute painful scrotum: ultrasound evaluation." Radiologic Clinics of North America. 2004; 42(2):349-363.
* Middleton WD, Kurtz AB, Hertzberg BS.Ultrasound: The Requisites. 3rd ed. Elsevier, 2015.
-
NEW QUESTION # 99
Which structure is most likely shown in this image of the right lower quadrant?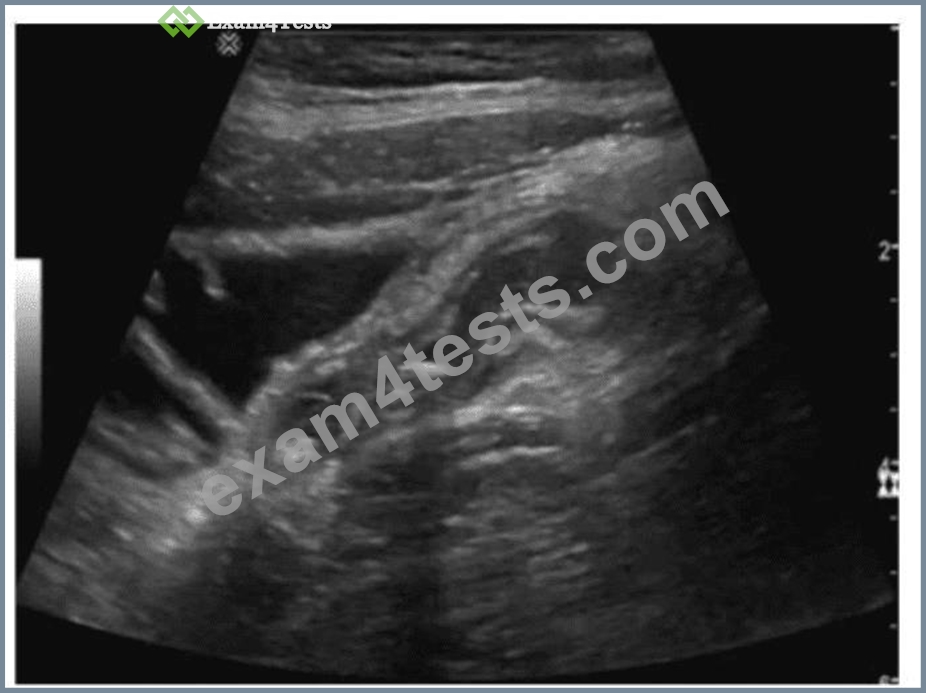
- A. Ureter
- B. Jejunum
- C. Appendix
- D. Fallopian tube
Answer: C
Explanation:
The ultrasound image shows a blind-ending, non-compressible, tubular structure in the right lower quadrant with a target or bullseye appearance in transverse section - highly suggestive of the appendix.
Sonographic features of the appendix (especially in suspected appendicitis):
* Blind-ending tubular structure arising from the cecum
* Non-compressible on graded compression
* Diameter >6 mm is suggestive of appendicitis
* May demonstrate a "target sign" in transverse view (concentric ring-like appearance)
* Increased echogenicity of surrounding fat in cases of inflammation
* May contain an appendicolith or show hyperemia on color Doppler if inflamed The location (right lower quadrant) and appearance in this case are classic for the normal or potentially inflamed appendix.
Differentiation from other options:
* A. Fallopian tube: Located more in the adnexal regions and usually not visible unless distended (e.g., hydrosalpinx).
* B. Ureter: Usually not visualized on ultrasound unless dilated due to obstruction.
* D. Jejunum: Has valvulae conniventes ("keyboard sign") and peristalsis; does not present with a blind- ending tubular appearance from the cecum.
References:
Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound. 5th Edition. Elsevier, 2018.
Chapter: Gastrointestinal Tract, pp. 460-468.
American College of Radiology (ACR). ACR Appropriateness Criteria - Right Lower Quadrant Pain - Suspected Appendicitis.
AIUM Practice Parameter for the Performance of a Pediatric Abdominal and/or Retroperitoneal Ultrasound Examination, 2020.
NEW QUESTION # 100
Which foreign body is better visualized with sonography than computed tomography (CT)?
- A. Metal
- B. Stone
- C. Wood
- D. Glass
Answer: C
Explanation:
Wooden foreign bodies are often difficult to detect on CT because of their low radiodensity, but they are highly echogenic with posterior shadowing or reverberation on ultrasound, making ultrasound superior for detecting retained wooden objects. Glass, metal, and stones are better visualized with CT due to their high radiodensity.
According to AIUM and musculoskeletal ultrasound literature:
"Wood is poorly visualized on CT but demonstrates high reflectivity and acoustic shadowing on ultrasound." Reference:
Bianchi S, Martinoli C. Ultrasound of the Musculoskeletal System. Springer, 2007.
AIUM Practice Parameter for Musculoskeletal Ultrasound, 2020.
-
NEW QUESTION # 101
What is the adrenal disorder that produces excessive secretion of aldosterone?
- A. Cushing disease
- B. Addison disease
- C. Conn syndrome
- D. Waterhouse-Friderichsen syndrome
Answer: C
Explanation:
Conn syndrome (primary hyperaldosteronism) results from excessive aldosterone secretion, often due to an adrenal adenoma, leading to hypertension, hypokalemia, and metabolic alkalosis. Cushing disease involves cortisol, Addison disease involves adrenal insufficiency, and Waterhouse-Friderichsen is associated with adrenal hemorrhage.
According to Rumack's Diagnostic Ultrasound:
"Conn syndrome is due to excessive secretion of aldosterone, often secondary to adrenal cortical adenoma." Reference:
Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound. 5th ed. Elsevier, 2017.
AIUM Practice Parameter for Adrenal Ultrasound, 2020.
-
NEW QUESTION # 102
Which structures converge to form the inferior vena cava?
- A. Right and left common iliac veins
- B. Right atrium and superior vena cava
- C. Right, left, and middle hepatic veins
- D. Superior mesenteric and splenic veins
Answer: A
Explanation:
The inferior vena cava (IVC) is formed by the confluence of the right and left common iliac veins at the level of approximately L5. The hepatic veins drain into the IVC superiorly but do not form it. The superior mesenteric and splenic veins join to form the portal vein, not the IVC.
According to Moore's Clinically Oriented Anatomy:
"The IVC begins at the level of L5 by the union of the right and left common iliac veins." Reference:
Moore KL, Dalley AF, Agur AMR. Clinically Oriented Anatomy. 8th ed. Wolters Kluwer, 2018.
Gray's Anatomy for Students, 4th ed., Elsevier, 2019.
-
NEW QUESTION # 103
Which condition results in the vascular abnormality shown in this image of a renal transplant?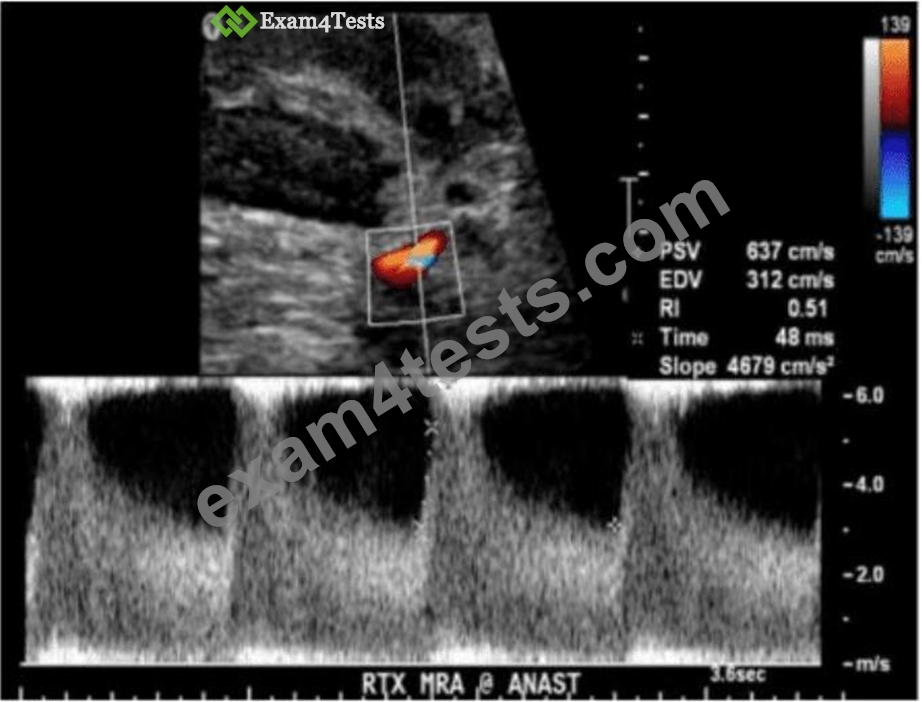
- A. Renal artery stenosis
- B. Arteriovenous malformation
- C. Iliac arteritis
- D. Renal vein thrombosis
Answer: A
Explanation:
The Doppler ultrasound image shows an elevated peak systolic velocity (PSV) of 637 cm/s, an elevated end- diastolic velocity (EDV) of 312 cm/s, and a low resistive index (RI) of 0.51 at the arterial anastomosis of a renal transplant. These findings are characteristic of significant renal artery stenosis (RAS) at the transplant vascular anastomosis.
Key sonographic features of renal artery stenosis:
* Peak systolic velocity (PSV) > 250-300 cm/s at the stenotic segment (this case: 637 cm/s)
* Post-stenotic turbulence with spectral broadening
* Low resistive index (RI < 0.56 suggests downstream vasodilation)
* Elevated acceleration time (AT > 0.07 sec), and reduced acceleration slope
* Aliasing on color Doppler due to high velocity
In this image, the marked increase in velocity with spectral aliasing and low RI is diagnostic of transplant renal artery stenosis - the most common vascular complication post-transplant, typically occurring at the site of surgical anastomosis.
Differentiation from other options:
* A. Iliac arteritis: A rare condition, not typically presenting with these Doppler changes.
* C. Renal vein thrombosis: Would show reversed or absent diastolic flow, not elevated systolic velocities.
* D. Arteriovenous malformation (AVM): Produces a high-velocity, low-resistance waveform but is associated with color bruit, aliasing, and pulsatile venous waveforms - not evident here.
References:
Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound. 5th Edition. Elsevier, 2018.
Chapter: Transplant Imaging, pp. 1035-1045.
American Institute of Ultrasound in Medicine (AIUM). Practice Parameter for the Performance of a Renal Artery Duplex Sonographic Examination, 2020.
Radiopaedia.org. Renal artery stenosis (transplant): https://radiopaedia.org/articles/renal-artery-stenosis- transplant
NEW QUESTION # 104
Which type of hernia is located medial to the inferior epigastric artery?
- A. Direct inguinal
- B. Spigelian
- C. Indirect inguinal
- D. Femoral
Answer: A
Explanation:
Direct inguinal hernias protrude through Hesselbach's triangle, which lies medial to the inferior epigastric artery. In contrast, indirect inguinal hernias pass lateral to the inferior epigastric artery via the deep inguinal ring.
According to Moore's Clinically Oriented Anatomy:
"Direct inguinal hernias occur medial to the inferior epigastric vessels, within Hesselbach's triangle." Reference:
Moore KL, Dalley AF, Agur AMR. Clinically Oriented Anatomy. 8th ed. Wolters Kluwer, 2018.
Gray's Anatomy for Students, 4th ed., Elsevier, 2019.
-
NEW QUESTION # 105
Which technique best differentiates a bladder mass from a hematoma?
- A. Use harmonic imaging
- B. Change patient position
- C. Obtain post-void image
- D. Fill the bladder
Answer: B
Explanation:
Changing the patient's position allows evaluation of lesion mobility. Blood clots and hematomas are often mobile, while true bladder wall masses remain fixed. This technique helps differentiate between solid masses and non-adherent debris.
According to Rumack's Diagnostic Ultrasound:
"Changing patient position may distinguish between mobile blood clots and fixed bladder wall masses." Reference:
Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound. 5th ed. Elsevier, 2017.
AIUM Practice Parameter for Bladder Ultrasound, 2020.
NEW QUESTION # 106
Which condition is most consistent with this image of a postsurgical breast?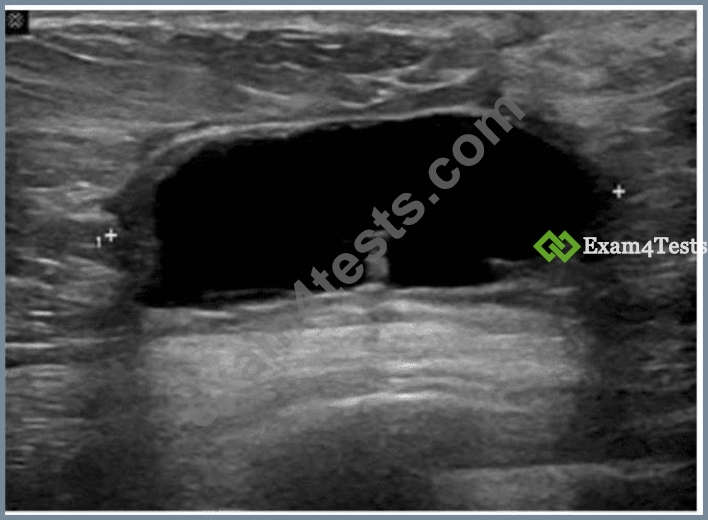
- A. Carcinoma
- B. Seroma
- C. Abscess
- D. Blood clot
Answer: B
Explanation:
The ultrasound image reveals a well-defined, anechoic (black), thin-walled fluid collection located in the subcutaneous or parenchymal plane of the breast. This is most consistent with a seroma, particularly in the context of recent breast surgery.
A seroma is a common postsurgical finding, representing a sterile collection of serous fluid that accumulates in the surgical bed. It typically appears:
* Anechoic (or hypoechoic if older)
* Well circumscribed
* Without internal septations or debris
* Lacking hyperemia or surrounding inflammatory changes
This contrasts with:
* A. Carcinoma - typically presents as an irregular, hypoechoic mass with angular margins, internal vascularity, and shadowing.
* B. Blood clot (hematoma) - often appears heterogeneous, with internal echoes and variable echotexture depending on the age of the clot.
* C. Abscess - appears as a complex fluid collection with thick walls, internal debris, septations, and surrounding hyperemia (often with clinical signs of infection).
D: Seroma - Correct. The described anechoic, clean-walled fluid collection is classic for a postoperative seroma.
References:
Mendelson EB, Bohm-Velez M, Berg WA.ACR BI-RADS Atlas: Ultrasound. American College of Radiology; 2013.
Stavros AT. Breast Ultrasound. Lippincott Williams & Wilkins; 2004.
Rumack CM, Wilson SR, Charboneau JW, Levine D. Diagnostic Ultrasound, 5th ed. Elsevier; 2017.
NEW QUESTION # 107
......
Dumps Brief Outline Of The AB-Abdomen Exam: https://torrentpdf.exam4tests.com/AB-Abdomen-pdf-braindumps.html